
What Is Meth Psychosis? Symptoms, Timeline, and Treatment

Meth psychosis is a temporary break from reality caused by methamphetamine use, marked by paranoia, hallucinations, and false beliefs that feel completely real to the person experiencing them. Symptoms usually clear within days once meth use stops and sleep returns.
The experience frightens families who witness it. A person in this state may believe strangers are following them, hear voices no one else hears, or feel insects moving beneath the skin.
Meth psychosis is not the same condition as schizophrenia, though the two resemble each other closely enough that clinicians sometimes confuse them. What separates them is the trigger and how quickly symptoms fade once the drug clears.
Understanding what drives meth psychosis, how long it lasts, and which treatments work separates an episode that resolves from one that repeats.
Key Takeaways
- A meta-analysis of 17 studies covering 4,095 participants found methamphetamine-induced psychotic disorder in 36.5% of methamphetamine misusers, a figure reported by Wearne and Cornish in Frontiers in Psychiatry.
- McKetin’s prospective cohort in JAMA Psychiatry recorded a fivefold increase in the odds of psychotic symptoms during periods of methamphetamine use, climbing to elevenfold at 16 or more days of use within a single month.
- DSM-5-TR classifies the condition as stimulant-induced psychotic disorder and separates it from schizophrenia by its temporal link to stimulant use rather than by symptom appearance alone.
- Acute episodes typically resolve within days of abstinence, while a documented minority of people carry psychotic symptoms beyond one month.
- Antipsychotic medication controls acute symptoms, but contingency management and the Matrix Model form the evidence base that prevents recurrence.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Is Meth Psychosis?
Meth psychosis is a psychotic state that methamphetamine produces during intoxication or shortly afterward, defined by prominent delusions, hallucinations, or both. DSM-5-TR names this condition stimulant-induced psychotic disorder rather than meth psychosis, grouping methamphetamine with amphetamine and prescription stimulants.
The diagnosis rests on timing. Methamphetamine exposure precedes the symptoms, and the symptoms exceed what ordinary intoxication produces. When psychotic features persist roughly a month past acute intoxication and withdrawal, clinicians reassess for an independent psychotic disorder.
People describe the state in plain terms long before a clinician names it. Losing touch with reality, seeing things that are not there, and becoming convinced of threats that no one else perceives are the descriptions that bring families to treatment centers.
Researchers divide the condition into four recognized presentations. Acute meth psychosis emerges during or immediately after methamphetamine use and remits within days.
Subacute meth psychosis extends across several weeks in regular users, while persistent meth psychosis continues past one month and resembles a primary psychotic disorder. Recurrent meth psychosis returns after abstinence, triggered by stress or sleep loss rather than fresh exposure.
What Causes Meth Psychosis?
Meth psychosis develops when methamphetamine floods dopamine pathways beyond the brain’s capacity to regulate them, and genetic vulnerability, sleep loss, and trauma history determine which individuals cross that threshold. The National Institute on Drug Abuse documents psychotic symptoms as a recognized consequence of methamphetamine use.
How Methamphetamine Changes Dopamine Signaling
Methamphetamine disrupts VMAT2, the transporter that packages dopamine into storage vesicles, forcing dopamine into the cell body. The drug then reverses the dopamine transporter, pushing that dopamine outward into the synapse instead of retrieving it.
This flood overstimulates dopamine D2 receptors along the mesolimbic pathway, the circuit most people know as the brain’s reward pathway. Persecutory delusions and hallucinations emerge directly from that overstimulation.
A second mechanism explains why symptoms outlast the drug. Methamphetamine elevates glutamate release in the cortex, and excess glutamate damages GABAergic interneurons in the prefrontal cortex, the cells that normally restrain runaway signaling. Repeated exposure degrades that brake, which is why dopamine signaling remains unstable well after the last dose.
Genetic and Family History Risk Factors
Candidate genes linked to schizophrenia vulnerability overlap with genes linked to methamphetamine psychosis vulnerability, which explains why two people using identical amounts diverge sharply in outcome. A family history of a psychotic disorder elevates individual risk substantially.
McKetin’s cohort of 278 methamphetamine-dependent participants quantified how common the experience becomes in dependent users. Across four observed months, 60% reported psychotic symptoms at least once, with suspiciousness present in 71% of those reports, hallucinations in 51%, and delusions or unusual thoughts in 35%.
Sleep Deprivation, Trauma, and Environmental Triggers
Environmental conditions convert genetic vulnerability into an actual episode, and binge-pattern use supplies most of them at once.
Conditions that raise the likelihood of a psychotic episode:
- Sustained wakefulness during a binge deprives the brain of the sleep that clears psychotic symptoms, and people often remain awake for several consecutive days.
- High-dose and high-frequency use drives the strongest single effect, with McKetin recording elevenfold odds at 16 or more days of use in a month.
- Smoking or injecting methamphetamine delivers the drug to the brain faster than oral routes, producing steeper dopamine surges.
- Early age of first use alters neurodevelopment during a period when dopamine systems are still maturing.
- Adverse childhood experiences (ACEs) interact with methamphetamine use frequency to raise psychosis risk, a relationship Ding and colleagues documented directly.
- Frequent cannabis or alcohol use roughly doubles the odds of psychotic symptoms on top of methamphetamine alone.
Are you covered for treatment?


Better Life Recovery is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Co-Occurring Conditions That Raise Psychosis Risk
Certain psychiatric conditions occur alongside methamphetamine psychosis far more often than chance predicts, and each pairing carries a distinct mechanism.
Conditions that co-occur with methamphetamine psychosis and why:
- Mood disorders share dopaminergic and serotonergic disruption with stimulant use, and people frequently use methamphetamine to lift depressive states before dependence forms.
- Post-traumatic stress disorder generates hypervigilance that methamphetamine amplifies into frank paranoia, since both states heighten threat detection.
- Antisocial personality disorder correlates with earlier onset and heavier use patterns, which pushes cumulative exposure higher.
- Prior psychotic episodes leave a sensitized dopamine system that reaches the psychotic threshold at lower doses than before.
Rebecca McKetin, PhD, established the dose-response relationship that anchors modern understanding of this condition. Her 2013 JAMA Psychiatry study tracked methamphetamine-dependent participants who carried no lifetime diagnosis of schizophrenia or mania, which isolated the drug’s contribution from pre-existing psychiatric illness.
How Long Does Meth Psychosis Last?

Meth psychosis lasts hours to several days in most people once methamphetamine use stops, while a smaller group carries symptoms for weeks and a documented minority continues past one month.
Acute Meth Psychosis Timeline
The acute course follows a recognizable sequence tied to drug clearance and sleep recovery.
- Hours 0 to 24: Symptoms begin during or immediately after use. Agitation, suspiciousness, and sensory distortion appear first, often alongside sustained wakefulness.
- Days 1 to 2: Hallucinations typically begin receding once methamphetamine clears the body and the person sleeps. Sleep functions as an active clinical variable here, not an afterthought.
- Days 2 to 7: Most acute episodes resolve inside this window. The person may remain anxious, suspicious, or emotionally unsettled after the hallucinations stop.
- Weeks 2 to 3: Delusions and paranoia typically settle in people whose symptoms outlast the first week.
- Beyond one month: Persistence past this threshold prompts formal evaluation for an independent psychotic disorder under DSM-5-TR.
Persistent and Recurrent Meth Psychosis
A clinically significant subset carries psychotic symptoms for six months or longer after stopping methamphetamine. Chronic high-dose users account for most of these cases.
Repeated methamphetamine exposure produces behavioral sensitization, a reverse-tolerance state in which the brain responds more strongly to smaller amounts over time. Ujike and Sato described this progressive vulnerability pattern in methamphetamine users, and it explains an outcome families find bewildering.
Under sensitization, psychosis returns without fresh methamphetamine exposure. Stress, sleep deprivation, or a much smaller dose than before retriggers symptoms, sometimes after extended abstinence.
What Are the Symptoms of Meth Psychosis?

Meth psychosis produces persecutory delusions, auditory and visual hallucinations, and disorganized thinking, with tactile hallucinations appearing more often here than in most other psychotic states. A systematic review of 94 studies covering 7,387 participants found persecutory delusions and auditory and visual hallucinations reported in 65% to 84% of studies.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
Common Signs of Meth Psychosis
Symptoms that appear in most episodes:
- Persecutory delusions convince the person that specific people intend to harm, follow, or surveil them, and no evidence dislodges the belief.
- Auditory hallucinations present as voices commenting, threatening, or conversing, which families describe simply as hearing voices.
- Visual hallucinations occur more frequently in methamphetamine psychosis than in primary psychotic disorders, producing figures, movement, or shadows at the edge of vision.
- Formication creates the sensation of insects crawling beneath the skin, a tactile hallucination known on the street as meth mites or crank bugs, and it drives the compulsive skin picking that leaves visible sores.
- Ideas of reference lead the person to interpret unrelated events, broadcasts, or conversations as carrying direct personal meaning.
- Disorganized speech jumps between unconnected topics, which makes ordinary conversation difficult to follow.
Severe Symptoms and Emergency Warning Signs
Certain presentations require emergency medical care rather than observation at home. Calling 911 remains the correct response when any of the following appear, and the SAMHSA National Helpline operates 24 hours a day for guidance outside an emergency.
Signs that require emergency intervention:
- Acting on persecutory beliefs puts the person and others in immediate physical danger, because the perceived threat feels entirely real.
- Aggression or violence emerges from fear rather than intent, and it escalates unpredictably during an episode.
- Command hallucinations instruct the person to perform specific actions, and these carry elevated risk of harm.
- Any statement about ending one’s life demands immediate emergency response without exception.
- Catatonic or unresponsive states indicate a medical emergency requiring hospital evaluation.
- High body temperature combined with agitation signals possible stimulant toxicity, which becomes life-threatening quickly.
- Punding describes stereotyped repetitive behavior such as compulsively sorting, arranging, or disassembling objects for hours, and it marks advanced stimulant intoxication.
Long-Term Effects of Repeated Psychotic Episodes
Consequences that accumulate across repeated episodes:
- Cognitive impairment affects set-shifting, memory recall, and response inhibition, and these deficits track with duration and severity of methamphetamine dependence.
- Progression to a primary psychotic disorder occurs in a meaningful proportion of people whose symptoms persist, which changes both diagnosis and long-term treatment.
- Negative symptoms such as flattened affect and social withdrawal appear in roughly a quarter of methamphetamine-associated psychosis cases, less often than in schizophrenia but frequently enough to matter clinically.
- Lowered psychosis threshold results from behavioral sensitization, meaning each subsequent episode requires less methamphetamine to trigger.
Meth Psychosis vs Schizophrenia: How to Tell the Difference
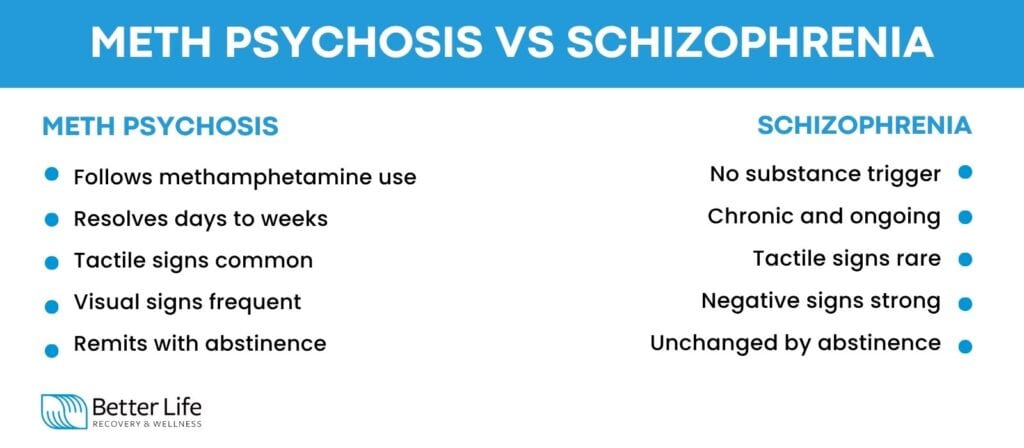
Meth psychosis and schizophrenia differ primarily in what triggers the symptoms and whether abstinence resolves them, since the symptom picture itself overlaps heavily. The overlap runs deep enough that misdiagnosis occurs in both directions.
| Feature | Meth Psychosis | Schizophrenia |
|---|---|---|
| Onset trigger | Follows methamphetamine use | Requires no substance trigger |
| Typical duration | Days to weeks after abstinence | Chronic and ongoing |
| Tactile hallucinations | Common | Uncommon |
| Visual hallucinations | More frequent | Less frequent |
| Negative symptoms | Present in a minority | Prominent and persistent |
| Formal thought disorder | Less pronounced | More pronounced |
| Response to abstinence | Symptoms typically remit | Symptoms continue unchanged |
Three pieces of evidence resolve the question in practice. Reconstructing the timeline of methamphetamine use against symptom onset, confirming recent use through urine toxicology, and gathering collateral history from family members together distinguish the two conditions more reliably than symptom observation alone.
Bipolar I disorder with psychotic features forms the second differential. Manic episodes generate grandiosity, reduced sleep, and psychotic symptoms that resemble stimulant intoxication, but the mood elevation precedes and outlasts any substance use.
How Is Meth Psychosis Diagnosed?
Clinicians diagnose meth psychosis by establishing a temporal relationship between methamphetamine use and psychotic symptoms, then confirming that relationship with objective testing and collateral history.
The Positive and Negative Syndrome Scale (PANSS) rates symptom severity across positive symptoms, negative symptoms, and general psychopathology. Clinical trials in methamphetamine psychosis use reduction in PANSS total score as their primary endpoint.
The Brief Psychiatric Rating Scale (BPRS) serves a similar function and supplied the outcome measure in McKetin’s cohort. There, a score of 4 or higher on suspiciousness, hallucinations, or unusual thought content defined a clinically significant symptom.
Urine toxicology confirms recent methamphetamine exposure objectively rather than relying on self-report. Collateral history from family members fills gaps that a person in an active episode cannot supply, and the DSM-5-TR one-month rule then determines whether the diagnosis holds or shifts to an independent psychotic disorder.
Are you covered for treatment?
Better Life Recovery is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!What Is the ICD-10 Code for Meth-Induced Psychosis?
No methamphetamine-specific ICD-10 code exists. Methamphetamine, amphetamine, and prescription stimulants all fall under the F15 category for other stimulant related disorders, while cocaine occupies a separate F14 category.
Three codes cover stimulant-induced psychotic disorder, and the correct one depends on whether a stimulant use disorder accompanies the psychosis.
| Code | ICD-10-CM description | Clinical situation |
|---|---|---|
| F15.159 | Other stimulant abuse with stimulant-induced psychotic disorder, unspecified | With mild stimulant use disorder |
| F15.259 | Other stimulant dependence with stimulant-induced psychotic disorder, unspecified | With moderate or severe stimulant use disorder |
| F15.959 | Other stimulant use, unspecified with stimulant-induced psychotic disorder, unspecified | Without a stimulant use disorder |
The final digit specifies the presentation. A trailing 0 designates psychotic disorder with delusions and a trailing 1 designates psychotic disorder with hallucinations, so F15.251 codes stimulant dependence with stimulant-induced psychotic disorder with hallucinations.
How Is Meth Psychosis Treated?
Treatment for meth psychosis controls the acute episode with antipsychotic medication and prevents recurrence with behavioral treatment for the underlying stimulant use disorder. A review of the epidemiology and management of methamphetamine psychosis identifies psychosocial treatment as the optimal first-line approach.
Olanzapine, quetiapine, risperidone, aripiprazole, paliperidone extended-release, and haloperidol all reduced acute symptoms across six randomized controlled trials covering 314 participants. A network meta-analysis placed olanzapine and quetiapine ahead of risperidone, and olanzapine produces fewer extrapyramidal symptoms than haloperidol. Benzodiazepines supplement antipsychotics for agitation.
Medication alone does not prevent recurrence, because continued methamphetamine use retriggers psychosis. Contingency management holds the strongest evidence base for stimulant use disorder, alongside the Matrix Model, Cognitive Behavioral Therapy, and Motivational Enhancement Therapy. Restoring sleep functions as active treatment rather than supportive care.
No medication holds FDA approval for methamphetamine use disorder. Naltrexone combined with bupropion produced a modest response advantage over placebo in the ADAPT-2 trial reported by Trivedi and colleagues, while N-acetylcysteine and repetitive transcranial magnetic stimulation remain investigational. All three target the stimulant use disorder rather than psychosis directly.
Meth Psychosis Treatment at Better Life Recovery
Better Life Recovery provides outpatient stimulant use disorder and mental health treatment for adults 18 and over at 25A Hanover Rd in Florham Park, New Jersey. The facility operates outpatient programs only, with no on-site detoxification and no residential services.
Someone in an active psychotic episode requires medical stabilization first. Better Life Recovery assists with placement into detox or stabilization, then admits the person into partial care, intensive outpatient, or outpatient programming once stabilized.
Methamphetamine psychosis alongside stimulant use disorder is a co-occurring presentation, which places it within dual diagnosis treatment. Clients in partial care and intensive outpatient complete the PHQ-9 and GAD-7 weekly, and the intake battery includes the Columbia Suicide Severity Rating Scale among 10 assessments conducted on site.
Sharon Cartwright, LPC, LCADC, ACS, CCS, NCC, Clinical Director at Better Life Recovery, brings more than a decade of experience across detoxification, residential, halfway house, and intensive outpatient settings.
“The first clinical question is always whether the symptoms track the substance use or run independently of it,” Cartwright said. “That answer reshapes the treatment plan. Someone whose paranoia lifts with sustained abstinence needs something different from someone whose symptoms hold steady after the stimulant clears.”
Frequently Asked Questions
What does meth psychosis feel like to the person experiencing it?
The experience feels entirely real rather than imagined, which is why reassurance rarely works. People describe overwhelming certainty that they are being watched or pursued, combined with sensory experiences no one else shares. Insight is usually absent during the episode, meaning the person cannot recognize the symptoms as symptoms until afterward.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
Can meth psychosis become permanent?
Meth psychosis resolves within weeks for most people, but a documented minority carries symptoms for six months or longer. When psychotic features persist well past abstinence, clinicians reassess the diagnosis and may identify an independent psychotic disorder that requires ongoing psychiatric treatment rather than substance use treatment alone.
Can meth psychosis come back after months of sobriety?
Yes. Behavioral sensitization leaves the dopamine system reactive long after methamphetamine use stops, so psychotic symptoms can return without fresh exposure. Documented triggers include significant stress, extended sleep deprivation, and doses far smaller than those that caused the original episode.
What should a family member do during a meth psychosis episode?
Calling 911 is appropriate whenever violence, unresponsiveness, high body temperature with agitation, or any statement about self-harm appears. Otherwise, reducing stimulation, avoiding argument about the delusion, and moving to a calm environment help. Personal safety comes first, and leaving is the right choice if the situation escalates.
Can meth psychosis be treated at home?
Acute psychosis requires medical evaluation rather than home management, because distinguishing stimulant toxicity from other emergencies needs clinical assessment. Mild symptoms sometimes resolve with sleep and abstinence, but no reliable way exists for a family member to determine severity without professional input.
Can a person have both meth psychosis and schizophrenia?
Yes, and this combination complicates diagnosis considerably. Someone with an existing schizophrenia diagnosis who uses methamphetamine experiences symptom exacerbation on top of their baseline condition. Treatment then addresses both the primary psychotic disorder and the stimulant use disorder simultaneously rather than treating one and deferring the other.
Are you covered for treatment?
Better Life Recovery is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Are men or women more likely to develop meth psychosis?
Studies of hospitalized methamphetamine users skew heavily male, though this pattern reflects use rates and treatment-seeking behavior more than biological susceptibility. Research has not established a clear sex-based difference in vulnerability once frequency, dose, and duration of methamphetamine use are accounted for.
Does sleep deprivation cause meth psychosis by itself?
Extended sleep deprivation alone produces perceptual disturbances and paranoid thinking in otherwise healthy people. During methamphetamine binges the two factors compound, because the drug both drives dopamine excess and eliminates sleep. Restoring sleep resolves a substantial portion of acute symptoms.
References
- McKetin, R., Lubman, D. I., Baker, A. L., Dawe, S., & Ali, R. L. (2013). Dose-related psychotic symptoms in chronic methamphetamine users: Evidence from a prospective longitudinal study. JAMA Psychiatry, 70(3), 319–324.
- Wearne, T. A., & Cornish, J. L. (2018). A comparison of methamphetamine-induced psychosis and schizophrenia: A review of positive, negative, and cognitive symptomatology. Frontiers in Psychiatry, 9, 491.
- Glasner-Edwards, S., & Mooney, L. J. (2014). Methamphetamine psychosis: Epidemiology and management. CNS Drugs, 28(12), 1115–1126.
- Arunogiri, S., Foulds, J. A., McKetin, R., & Lubman, D. I. (2018). A systematic review of risk factors for methamphetamine-associated psychosis. Australian & New Zealand Journal of Psychiatry, 52(6), 514–529.
- Voce, A., Calabria, B., Burns, R., Castle, D., & McKetin, R. (2019). A systematic review of the symptom profile and course of methamphetamine-associated psychosis. Substance Use & Misuse, 54(4), 549–559.
- Verachai, V., Rukngan, W., Chawanakrasaesin, K., Nilaban, S., Suwanmajo, S., Thanateerabunjong, R., Kaewkungwal, J., & Kalayasiri, R. (2014). Treatment of methamphetamine-induced psychosis: A double-blind randomized controlled trial comparing haloperidol and quetiapine. Psychopharmacology, 231(16), 3099–3108.
- Xue, X., Song, Y., Yu, X., Fan, Q., Tang, J., & Chen, X. (2018). Olanzapine and haloperidol for the treatment of acute symptoms of mental disorders induced by amphetamine-type stimulants: A randomized controlled trial. Medicine, 97(8), e9786.
- Cohen-Laroque, J., Grangier, I., & Perez, N. (2024). Positive and negative symptoms in methamphetamine-induced psychosis compared to schizophrenia: A systematic review and meta-analysis. Schizophrenia Research, 267, 182–190.
- Trivedi, M. H., Walker, R., Ling, W., Dela Cruz, A., Sharma, G., Carmody, T., Ghitza, U. E., Wahle, A., Kim, M., Shores-Wilson, K., Sparenborg, S., Coffin, P., Schmitz, J., Wiest, K., Bart, G., Sonne, S. C., Wakhlu, S., Rush, A. J., Nunes, E. V., & Shoptaw, S. (2021). Bupropion and naltrexone in methamphetamine use disorder. New England Journal of Medicine, 384(2), 140–153.
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Publishing.
- Centers for Medicare & Medicaid Services and National Center for Health Statistics. (2026). ICD-10-CM: F15, other stimulant related disorders.
Medically reviewed by Sharon Cartwright, LPC, LCADC, ACS, CCS, NCC, Clinical Director at Better Life Recovery. Last reviewed August 21, 2026.
Share This Post

Better Life Recovery
All author posts
TREATMENTS WE OFFER
Are you covered for treatment?


Better Life Recovery is an approved provider for Blue Shield of California and Magellan, while also accepting many other major insurance carriers.
Check Coverage Now!

