
Binge Drinking vs Alcoholism: Where the Line Actually Falls

Binge drinking and alcoholism describe two different things. Binge drinking describes how much a person drinks in one sitting. Alcoholism describes whether that person can stop.
The two overlap, which is why the words get used interchangeably. Most people who binge drink, though, do not meet the medical criteria for a drinking disorder.
That distinction matters to anyone quietly wondering which side of the line they fall on. It changes what the risk looks like and what kind of help makes sense.
The line is not drawn by counting drinks. It is drawn by looking at control, consequences, and what happens when someone tries to stop.
Key Takeaways
- A CDC analysis of 138,100 adults by Esser and colleagues found alcohol dependence in 10.5% of binge drinkers, meaning roughly nine in ten people who binge drink do not meet dependence criteria.
- Dependence appears in 1.3% of adults who do not binge drink, so binge drinking multiplies the risk roughly eightfold even though it does not equal a disorder.
- The National Institute on Alcohol Abuse and Alcoholism defines binge drinking as a pattern reaching 0.08% blood alcohol concentration. That corresponds to about 5 drinks for men or 4 for women in roughly two hours.
- DSM-5-TR diagnoses alcohol use disorder when a person meets 2 or more of 11 criteria within a 12-month period, graded mild, moderate, or severe.
- Binge drinking, heavy drinking, and moderate drinking describe consumption, while alcohol use disorder describes a person’s relationship with alcohol.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Is Binge Drinking?
Binge drinking is a pattern of alcohol consumption that raises blood alcohol concentration to 0.08% or higher. For most adults that means about 5 drinks for men or 4 for women within roughly two hours. The National Institute on Alcohol Abuse and Alcoholism frames it as a pattern rather than a single event.
A standard drink in the United States contains 0.6 fluid ounces of pure alcohol. Every threshold in this article counts standard drinks, not glasses or servings, and the two rarely match.
The definition rests on a measurable outcome rather than a moral judgment. Reaching that blood alcohol level produces measurable impairment regardless of how the person feels or how well they believe they are handling it.
What Counts as Binge Drinking for a Woman?
For women, the binge threshold is 4 or more standard drinks in about two hours, one drink lower than the male threshold. The difference is physiological rather than arbitrary.
Two mechanisms drive it. Women carry lower total body water, which concentrates alcohol in a smaller volume of fluid.
Women also produce less gastric alcohol dehydrogenase, the stomach enzyme that breaks down a portion of alcohol before it reaches the bloodstream.
Frezza and colleagues documented this second mechanism in the New England Journal of Medicine, showing that reduced first-pass metabolism in the stomach delivers more alcohol into circulation. The same amount of alcohol therefore produces a higher blood alcohol concentration in women than in men of equal weight.
What Is High-Intensity Drinking?
High-intensity drinking is the NIAAA term for consumption at two or more times the binge threshold. It sits above binge drinking on the same scale rather than forming a separate category.
The distinction carries clinical weight. High-intensity drinking multiplies the risk of alcohol poisoning and emergency department admission well beyond the risk that standard binge drinking carries.
Moderate, Binge, and Heavy Drinking: How the Patterns Differ
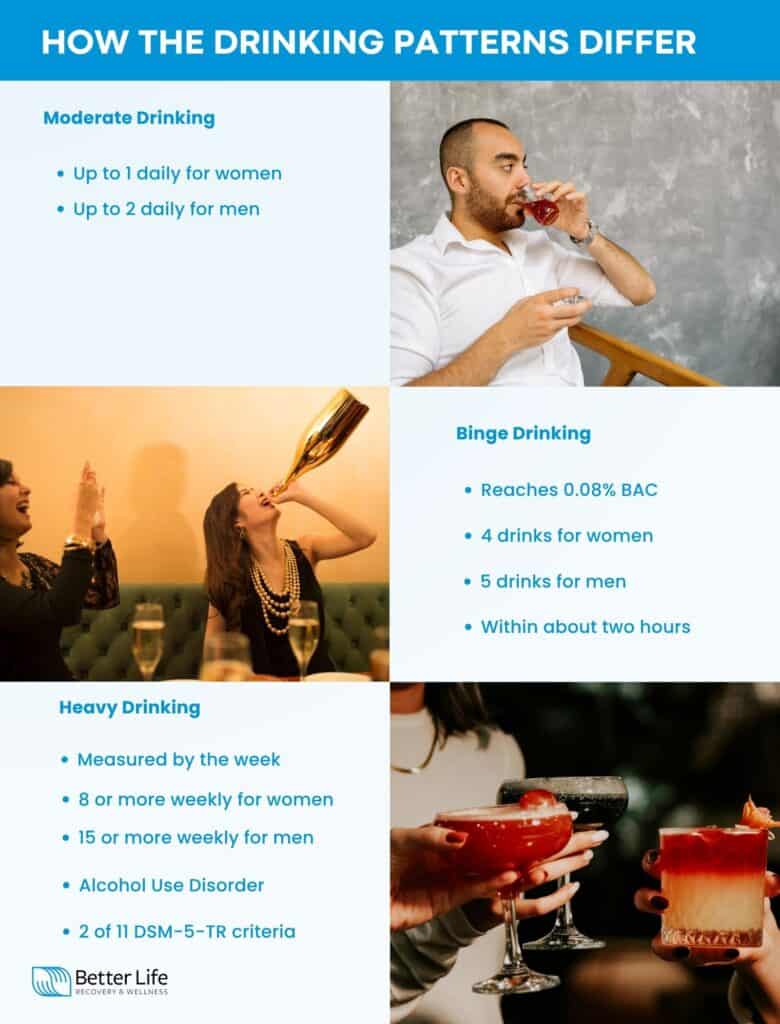
Moderate drinking, binge drinking, and heavy drinking are three separate measurements of consumption, and a person can meet one, several, or none of them. Each uses a different unit of time, which is why the definitions look inconsistent until they are placed side by side.
| Pattern | Measured by | Defined as |
|---|---|---|
| Moderate drinking | The day | Up to 1 drink daily for women, up to 2 for men |
| Binge drinking | The clock, per occasion | Reaching 0.08% blood alcohol, about 4 or 5 drinks in two hours |
| Heavy drinking | The calendar, per week | 8 or more drinks weekly for women, 15 or more for men |
| Alcohol use disorder | Diagnostic criteria | 2 or more of 11 DSM-5-TR criteria within 12 months |
The first three rows describe how much a person drinks. The fourth describes something different, which is whether alcohol has taken hold of their choices.
A weekend drinker can meet the binge definition without ever reaching the heavy drinking threshold. Someone drinking two glasses of wine every evening can meet the heavy drinking threshold without ever binge drinking.
Binge Drinker vs Alcoholic: Where the Line Actually Falls
Binge drinking is not a form of alcoholism. Binge drinking is a pattern of consumption, while alcohol use disorder is a medical diagnosis, and the two are measured by entirely different instruments.
| Dimension | Binge Drinking | Alcohol Use Disorder |
|---|---|---|
| What it describes | A drinking pattern | A medical diagnosis |
| Measured by | Drinks per occasion and time | 11 DSM-5-TR criteria |
| Control between episodes | Usually intact | Impaired despite consequences |
| Withdrawal on stopping | Typically absent | Common in moderate to severe cases |
| Cravings | Situational | Persistent |
| Daily function | Often unaffected between episodes | Progressively disrupted |
| Overlap | About 1 in 10 meet dependence criteria | Many, though not all, binge drink |
The practical test is not volume. A person who drinks heavily on Saturday and gives it no thought until the following Saturday occupies a different clinical position from a person who drinks less but thinks about it constantly.
Esser and colleagues quantified the gap. Among binge drinkers, 10.5% met dependence criteria, which means the large majority of people crossing the binge threshold are not dependent on alcohol.
Are you covered for treatment?


Better Life Recovery is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Is Binge Drinking Worse Than Daily Drinking?
Neither pattern is safe, and neither is uniformly worse than the other. They concentrate risk in different places, which is why comparing them as better or worse produces a misleading answer.
Binge drinking concentrates risk into acute events. Injury, alcohol poisoning, blackout, and impaired decisions all cluster around the hours of the episode itself.
Daily drinking concentrates risk into accumulation. Liver damage, cardiovascular strain, and physical dependence build quietly over months, and dependence brings withdrawal when a person tries to stop.
The two frequently coexist. A person drinking daily who also exceeds the binge threshold on weekends carries both risk profiles at once rather than trading one for the other.
Why Do Some Binge Drinkers Develop Alcohol Use Disorder?

Binge drinking raises the risk of alcohol use disorder substantially without guaranteeing it, and three factors separate the people who progress from the people who do not.
Frequency and Quantity
Frequency predicts progression more reliably than any single episode does. Repeated binge episodes drive tolerance upward, and rising tolerance pushes consumption higher to produce the same effect.
That escalation establishes the loop that defines dependence. Changes in brain chemistry follow repeated heavy exposure, reshaping how the reward system responds to alcohol and to everything else.
Age of First Use and Family History
Earlier onset of heavy drinking predicts higher lifetime risk, because alcohol reaches a brain still completing its development. Family history compounds the effect independently.
A parent or sibling with alcohol use disorder raises individual risk regardless of drinking pattern. Genetic vulnerability and heavy exposure together produce a steeper trajectory than either produces alone.
Drinking to Manage Mood
Motive predicts progression more sharply than quantity. Drinking to celebrate carries a different trajectory from drinking to quiet anxiety, dull grief, or force sleep.
Patterns that signal higher risk of progression:
- Drinking to fall asleep establishes a nightly requirement, and alcohol degrades sleep architecture, which deepens the fatigue that prompts the next drink.
- Drinking to reduce anxiety produces rebound anxiety as blood alcohol falls, creating a cycle that intensifies with repetition.
- Drinking alone with regularity removes the social context that ordinarily limits how much a person consumes.
- Drinking to function at work or in relationships marks a shift from choosing alcohol to needing it.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
What Happens to the Body as Blood Alcohol Rises?
Calling 911 is the correct response whenever a person who has been drinking becomes unresponsive, vomits while semiconscious, breathes irregularly, or cannot be woken. The SAMHSA National Helpline operates 24 hours a day for guidance outside an emergency.
Blood alcohol concentration tracks impairment closely, and the effects escalate in a recognizable sequence.
| Blood alcohol | What happens | What to do |
|---|---|---|
| 0.02 to 0.05 | Mild relaxation, slower reaction time, early loss of judgment | Stop driving. Impairment is already measurable |
| 0.06 to 0.15 | Impaired coordination and speech, and the range where blackouts begin | Stop drinking. Do not leave the person alone |
| 0.16 to 0.30 | Vomiting, confusion, loss of the gag reflex, choking risk | Turn the person onto their side. Call 911 if unresponsive |
| Above 0.30 | Breathing and heart rate suppressed, unconsciousness, medical emergency | Call 911 immediately |
Blackouts deserve particular attention because people misread them. A blackout is anterograde amnesia, meaning the brain stops forming new memories while the person continues walking, talking, and making decisions. Wetherill and Fromme documented the mechanism, which involves disrupted hippocampal encoding rather than loss of consciousness.
Rising blood alcohol also explains why sobering up quickly does not work. The body eliminates alcohol through zero-order kinetics, clearing a roughly fixed amount per hour regardless of how much is present, so coffee, cold showers, and food change alertness without lowering blood alcohol. Sustained high levels produce alcohol poisoning, which suppresses the reflexes that protect the airway.
How Clinicians Actually Draw the Line
Clinicians separate a drinking pattern from a disorder through structured screening followed by diagnostic interview, not by counting drinks.
The Alcohol Use Disorders Identification Test (AUDIT) is a 10-item screen developed by the World Health Organization that measures consumption, dependence indicators, and alcohol-related harm. Higher scores signal a greater likelihood of hazardous drinking and prompt fuller assessment. The CAGE questionnaire offers a four-item alternative used when time is short.
Screening identifies risk rather than confirming diagnosis. A clinician then interviews against the 11 DSM-5-TR criteria, examining control, cravings, tolerance, withdrawal, and whether drinking has displaced other responsibilities. The AUDIT functions as the entry point to that conversation.
Alcohol Treatment at Better Life Recovery

Better Life Recovery provides outpatient alcohol and mental health treatment for adults 18 and over at 25A Hanover Rd in Florham Park, New Jersey. The facility operates outpatient programs only, with no on-site detoxification and no residential services.
Anyone experiencing alcohol withdrawal requires medical stabilization first, since withdrawal from physical dependence carries genuine risk. Better Life Recovery assists with placement into detox, then admits the person into partial care, intensive outpatient, or outpatient programs in New Jersey once stabilized.
Measurement-based care tracks progress throughout. Clients in partial care and intensive outpatient complete the PHQ-9 for depression and the GAD-7 for anxiety weekly, and the intake battery includes 10 assessments conducted on site.
Sharon Cartwright, LPC, LCADC, ACS, CCS, NCC, Clinical Director at Better Life Recovery, brings more than a decade of experience across detoxification, residential, halfway house, and intensive outpatient settings.
“People arrive convinced the question is how much they drink, and that is almost never the question we end up working on,” Cartwright said. “What tells us more is what happens in the days between. Whether alcohol occupies any space in someone’s thinking when they are not drinking is far more informative than the number of drinks.”
Frequently Asked Questions
What does it feel like when binge drinking starts becoming dependence?
The shift is usually quiet rather than dramatic. People describe alcohol occupying more mental space between occasions, planning around whether it will be available, and finding that stopping after one or two has become effortful rather than automatic. Physical signs such as morning shakiness appear later.
Are you covered for treatment?
Better Life Recovery is an approved provider for Blue Cross Blue Shield and Cigna, while also accepting many other major insurance carriers.
Check Coverage Now!Are all binge drinkers alcoholics?
No. Research on 138,100 adults found that about nine in ten binge drinkers do not meet criteria for alcohol dependence. Binge drinking still raises the risk of developing a disorder roughly eightfold compared with people who do not binge drink, so the pattern warrants attention on its own terms.
Can a person die from drinking too much alcohol?
Yes. Alcohol poisoning suppresses breathing, heart rate, and the gag reflex, and death can occur while a person appears to be sleeping it off. Anyone who cannot be woken, breathes irregularly, or vomits while semiconscious needs emergency medical care immediately.
Can binge drinking damage health without a diagnosis?
Yes, and this is the most common misunderstanding about the pattern. Binge drinking raises the risk of injury, cardiovascular strain, certain cancers, and liver damage independently of whether a person meets diagnostic criteria. The absence of a disorder does not mean the absence of harm.
How long does it take for binge drinking to become a disorder?
No fixed timeline exists, because progression depends on frequency, quantity, age of onset, genetics, and motive for drinking. Some people binge drink for years without progressing. Others develop symptoms within months, particularly when drinking serves to manage anxiety, grief, or sleep.
When should someone talk to a doctor about their drinking?
Reasonable triggers include repeatedly drinking more than intended, unsuccessful attempts to cut back, drinking that interferes with work or relationships, and any morning shakiness or nausea. Wondering whether drinking has become a problem is itself a legitimate reason to raise it with a physician.
Did you know most health insurance plans cover substance use disorder treatment? Check your coverage online now.
Can a person cut back on their own, or is treatment needed?
Many people reduce their drinking without formal treatment, particularly earlier in the pattern. Physical dependence changes that calculation, because stopping abruptly can trigger dangerous withdrawal. Anyone experiencing tremors, sweating, or agitation when not drinking should consult a physician before reducing intake.
Is binge drinking more common in college students than in adults?
Binge drinking peaks among adults aged 18 to 34 rather than among college students specifically. CDC surveillance places overall adult prevalence around 17%, with rates higher among men than women. Enrollment status matters less than age and social environment.
Does building a tolerance mean someone is becoming an alcoholic?
Tolerance is one of the 11 DSM-5-TR criteria, not a diagnosis by itself. Needing more alcohol for the same effect indicates the body has adapted to regular exposure. It becomes clinically significant when it appears alongside impaired control, cravings, or continued drinking despite consequences.
References
- Esser, M. B., Hedden, S. L., Kanny, D., Brewer, R. D., Gfroerer, J. C., & Naimi, T. S. (2014). Prevalence of alcohol dependence among US adult drinkers, 2009–2011. Preventing Chronic Disease, 11, E206.
- National Institute on Alcohol Abuse and Alcoholism. Understanding alcohol drinking patterns. National Institutes of Health.
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.). American Psychiatric Publishing.
- Frezza, M., di Padova, C., Pozzato, G., Terpin, M., Baraona, E., & Lieber, C. S. (1990). High blood alcohol levels in women: The role of decreased gastric alcohol dehydrogenase activity and first-pass metabolism. New England Journal of Medicine, 322(2), 95–99.
- Wetherill, R. R., & Fromme, K. (2016). Alcohol-induced blackouts: A review of epidemiology, clinical relevance, and mechanisms. Alcoholism: Clinical and Experimental Research, 40(5), 922–935.
- Saunders, J. B., Aasland, O. G., Babor, T. F., de la Fuente, J. R., & Grant, M. (1993). Development of the Alcohol Use Disorders Identification Test (AUDIT). Addiction, 88(6), 791–804.
- Centers for Disease Control and Prevention. Alcohol: Chronic disease indicators. US Department of Health and Human Services.
- Substance Abuse and Mental Health Services Administration. National Survey on Drug Use and Health. US Department of Health and Human Services.
Medically reviewed by Sharon Cartwright, LPC, LCADC, ACS, CCS, NCC, Clinical Director at Better Life Recovery. Last reviewed August 21, 2026.
Share This Post

Better Life Recovery
All author posts
TREATMENTS WE OFFER
Are you covered for treatment?


Better Life Recovery is an approved provider for Blue Shield of California and Magellan, while also accepting many other major insurance carriers.
Check Coverage Now!

